Addiction Treatment Billing for Treatment Centers: Insurance, Claims, Denials & RCM
Addiction treatment billing is the revenue-cycle process used by detox, residential, PHP, IOP, outpatient SUD, and opioid-treatment programs to verify insurance, obtain authorization, document covered care, submit claims, resolve denials, and collect payment. Unlike routine claim submission, addiction treatment billing often depends on behavioral-health carve-outs, continued-stay authorization, level-of-care transitions, facility and clinician enrollment, professional versus institutional billing, and payer-specific SUD rules.
A treatment center can submit a technically clean claim and still go unpaid when the wrong behavioral-health payer was identified, authorization expired during treatment, a level-of-care transition was not reapproved, the facility or clinician was not eligible under the payer contract, or the clinical record did not support the billed service. That is why successful addiction treatment billing requires more than transmitting claims.
This guide covers the operational workflow behind addiction insurance billing, Medicaid billing, prior authorization, claim submission, common addiction treatment claim denials, payment posting, A/R, and addiction RCM. For detailed CPT, HCPCS H-codes, S-codes, units, and revenue-code definitions, use our separate Substance Abuse Billing Codes reference.
Looking for outsourced billing rather than a workflow guide? Explore ClaraRCM's Substance Abuse Billing Services for Treatment Providers for eligibility, claims, denial management, payment posting, and A/R support.
Addiction Treatment Programs This Billing Workflow Applies To
The same revenue-cycle principles apply across multiple addiction-treatment settings, but the payer, authorization, claim type, and billing methodology can change with the level of care. This guide is designed for U.S. organizations delivering substance use disorder treatment across the following settings.
What Addiction Treatment Billing Covers
Addiction treatment billing covers the administrative and financial work required to convert covered SUD treatment into correctly submitted and fully resolved claims. That process can include pre-admission insurance verification, behavioral-health payer identification, provider enrollment, authorization management, documentation controls, coding, professional or institutional claim production, denial resolution, payment posting, underpayment review, and accounts-receivable follow-up.
A complete addiction treatment billing workflow should establish clear ownership for:
- Eligibility and benefits: confirming active coverage, the responsible payer or behavioral-health administrator, network status, and patient responsibility.
- Credentialing and enrollment: verifying that the facility, billing entity, and relevant clinicians can bill the responsible payer.
- Authorization: tracking approved services, levels of care, dates, days, units, and continued-stay deadlines.
- Clinical documentation: ensuring the record supports the treatment delivered and the billed level of care.
- Claim production: matching the service to the appropriate claim pathway, payer ID, providers, codes, institutional fields, and authorization data.
- Claim follow-up: correcting front-end rejections and monitoring payer adjudication.
- Denials, payments, and A/R: identifying the root cause of unpaid claims, reconciling remittances, reviewing underpayments, and protecting filing and appeal deadlines.
Problems arise when these responsibilities are separated without reliable handoffs. If intake, utilization review, the clinical record, authorization tracking, and billing do not agree on the payer, dates, level of care, or provider, the claim may fail even when each department completed its own task.
Addiction Insurance Billing: Verification, Benefits, and Payer Routing
Addiction insurance billing begins by identifying which insurer or behavioral-health administrator is financially responsible for the patient's substance use disorder treatment. A member may carry one medical insurance card while SUD benefits are administered by another organization, network, or behavioral-health division.
How Does Addiction Insurance Billing Work?
A practical addiction insurance billing workflow begins by verifying active coverage and the responsible benefit administrator before treatment, then confirming network status, authorization requirements, level-of-care benefits, patient financial responsibility, and the correct claim destination.
- Verify active coverage. Confirm effective dates and whether the SUD benefit is active for the proposed treatment dates.
- Identify the responsible behavioral-health payer. Do not assume the medical payer ID is also the SUD claim destination.
- Confirm network and provider status. Check the facility and relevant clinician participation where required.
- Verify authorization and level-of-care requirements. Determine whether admission, continued stay, or level changes require approval.
- Document claim-routing details. Record payer ID, claim form, filing limit, portal or submission route, and reference information.
Addiction Treatment Billing Checklist Before Admission
- Active insurance coverage and effective dates
- Responsible SUD or behavioral-health administrator
- Correct electronic payer ID
- Facility network status
- Rendering clinician network status where applicable
- Covered detox, residential, PHP, IOP, or outpatient benefit
- Prior authorization or notification requirement
- Patient deductible, copayment, coinsurance, and out-of-pocket status
- Required utilization-review or continued-stay schedule
- Claim type and billing route
- Timely-filing and appeal deadlines
Record the verification source, date, representative or portal reference, and limitations of the response. Benefit verification is not a guarantee of payment, but a complete verification record helps the billing team investigate conflicts later.
Operational checkpoint: “Behavioral health covered” is not a complete verification result. The record should identify the responsible payer, network status, authorization pathway, treatment setting, patient responsibility, and claim route. See ClaraRCM's eligibility and benefits verification services.
In-Network vs. Out-of-Network Addiction Treatment Billing
In-network billing follows the provider's contracted reimbursement and participation requirements. Out-of-network billing can require additional verification of benefit availability, claim routing, assignment-of-benefits procedures, patient responsibility, reimbursement methodology, and applicable federal or state protections.
An out-of-network benefit does not by itself guarantee direct payment to the treatment center or a specific reimbursement amount. Confirm the plan, payer, contract status, and applicable legal requirements before presenting expected reimbursement to the patient.
Addiction Medicaid Billing for SUD Treatment Programs
Addiction Medicaid billing is highly state- and plan-specific. Medicaid programs may differ in covered SUD levels of care, provider qualifications, HCPCS codes, modifiers, units, authorization rules, documentation standards, claim types, fee schedules, and managed-care routing.
A billing rule used successfully in one state's Medicaid program should not be carried into another state—or even another managed-care plan within the same state—without verification.
Medicaid vs. Managed Medicaid
Fee-for-service Medicaid claims follow the state's applicable enrollment, coverage, coding, and submission rules. When the member is enrolled with a Medicaid managed-care organization, the plan may administer authorization, network participation, claim routing, appeals, and payment under additional plan-specific requirements.
What Treatment Centers Should Track for Medicaid Billing
| Medicaid billing item | What the treatment center should track | Why it matters |
|---|---|---|
| Enrollment | Facility, location, billing entity, clinician, taxonomy, and plan participation | A covered service can still deny when the billing or rendering entity is not eligible |
| Level of care | Detox, residential, PHP, IOP, outpatient, OTP, and other covered program definitions | Coverage and claim pathways can differ by treatment setting |
| Code and unit | State- or plan-approved CPT/HCPCS code and applicable per-diem, encounter, or timed unit | National code definitions do not establish state Medicaid coverage |
| Modifiers | Program, provider, telehealth, or state-required modifiers | Missing or incorrect modifiers can cause avoidable denials |
| Authorization | Initial approval, approved dates or units, continued-stay dates, and level changes | Authorization and claim dates must remain synchronized |
| Claim destination | State Medicaid versus managed-care plan payer ID and submission route | Wrong routing can consume timely-filing time before the error is discovered |
| Filing and appeal limits | Initial submission, corrected claim, reconsideration, and appeal deadlines | Recoverable claims can become contractual write-offs after deadlines pass |
Maintain a payer matrix that identifies the current provider manual, fee schedule, plan contract, authorization contacts, covered levels of care, codes, units, modifiers, claim route, filing limits, and appeal process.
Important: Medicaid rules are not national defaults. Always verify the current state Medicaid agency instructions and, when applicable, the member's managed-care plan requirements for the date of service.
How Medicare and Commercial Insurance Change Addiction Treatment Billing
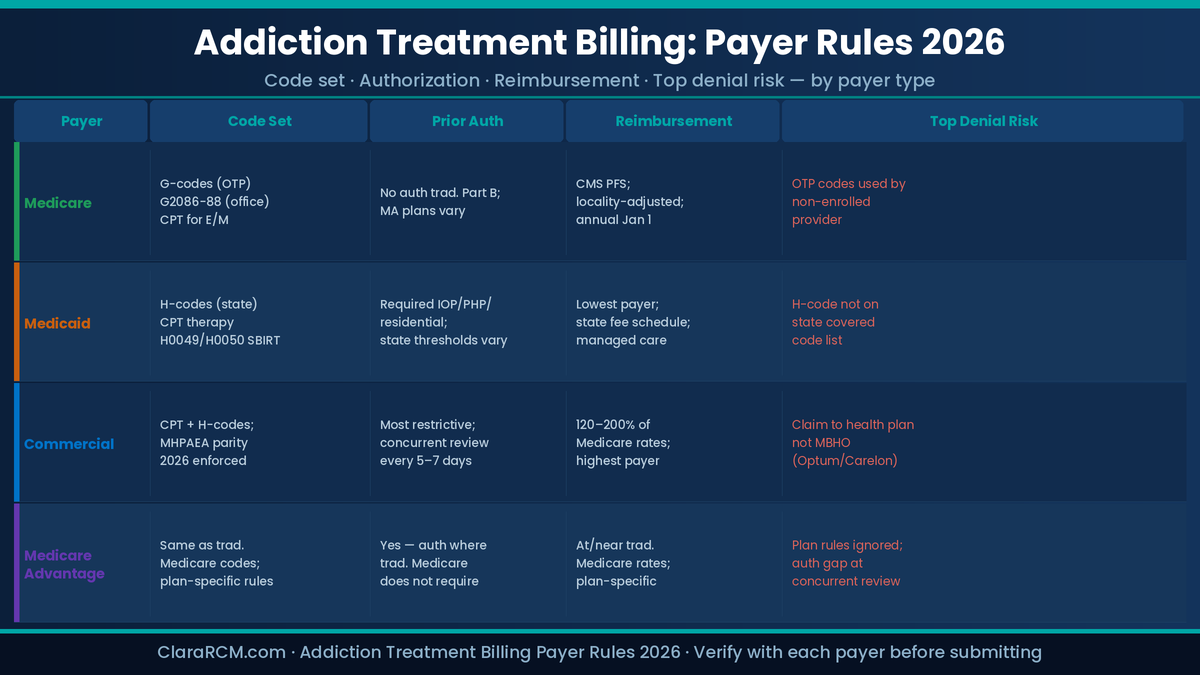
Addiction treatment billing changes substantially by payer. Traditional Medicare, Medicare Advantage, state Medicaid programs, Medicaid MCOs, and commercial behavioral-health plans can use different enrollment, authorization, claim-form, coding, documentation, and reimbursement rules for clinically similar treatment.
| Payer pathway | Operational priority | Frequent failure point | Pre-bill control |
|---|---|---|---|
| Medicare | Confirm the applicable Medicare benefit and provider enrollment pathway | Applying an OTP pathway to a provider that is not enrolled as a Medicare OTP | Validate provider type, enrollment, covered service, code pathway, and claims instructions |
| Medicaid | Build state- and plan-specific rules | Using a modifier, code, unit, or authorization rule from another state or MCO | Use the current state manual, fee schedule, MCO policy, and contract |
| Commercial | Identify the responsible behavioral-health entity and contracted arrangement | Wrong payer, authorization gaps, network conflicts, or unsupported level of care | Verify benefit administrator, network, authorization, claim route, and documentation criteria |
Medicare and Opioid Treatment Programs
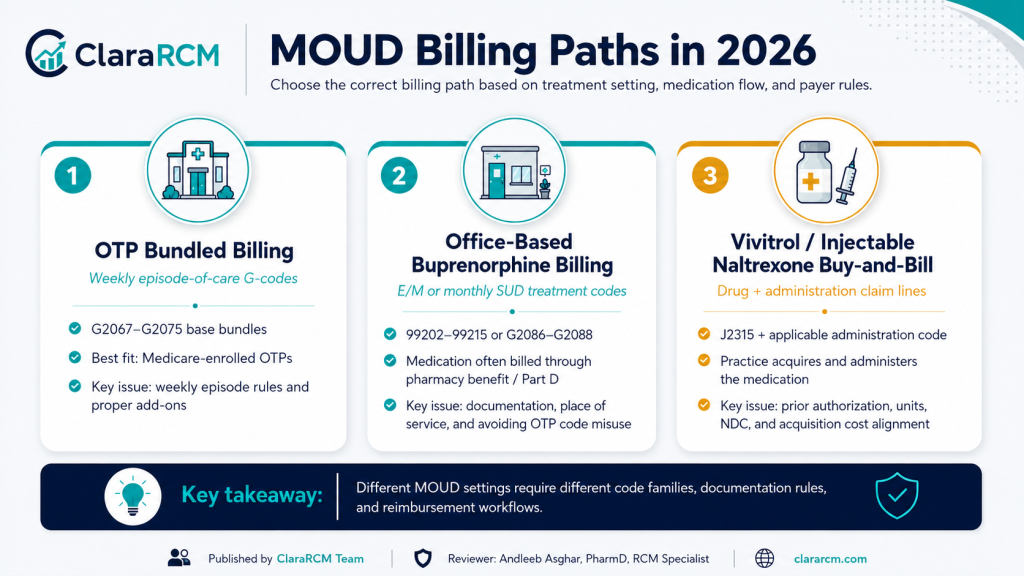
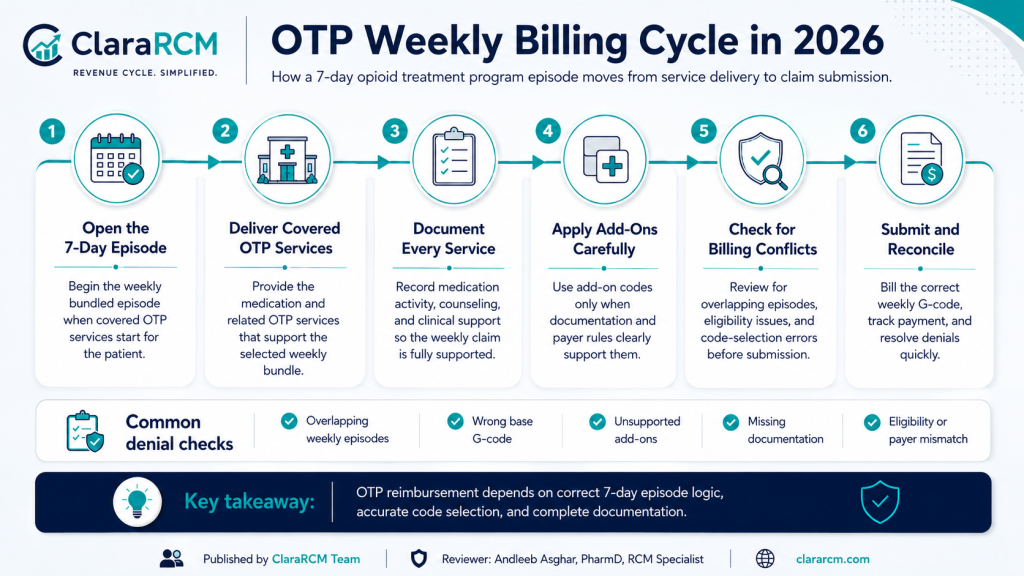
Medicare maintains separate payment pathways for office-based SUD treatment and Medicare-enrolled opioid treatment programs. An office-based practice treating OUD should not assume that OTP bundled billing applies simply because medication treatment is provided.
CMS currently describes G2086-G2088 as the monthly office-based SUD treatment pathway and separately maintains OTP weekly bundle and add-on billing requirements. :contentReference[oaicite:1]{index=1}
Commercial Addiction Treatment Billing
Commercial plans may administer SUD benefits internally or through a behavioral-health organization. Network participation can also differ between the facility and individual clinicians. Verify the benefit administrator and contracted arrangement before assuming that the company shown on the medical insurance card will adjudicate the SUD claim.
Addiction Treatment Billing by Level of Care
The treatment setting changes what the billing team must verify. A clinical level of care does not automatically determine one code or claim form, but it affects authorization, facility requirements, program documentation, reimbursement structure, and claim configuration.
| Level of care | Main billing risks | High-value control |
|---|---|---|
| Detox / withdrawal management | Incorrect setting, medical-intensity mismatch, authorization gaps, facility eligibility | Verify approved setting, dates, provider/program eligibility, and payer pathway |
| Residential treatment | Expired authorized days, wrong facility classification, inconsistent census or discharge dates | Reconcile patient census, authorization, contract, level of care, and billed dates before release |
| PHP | Program intensity, payer methodology, authorization changes, institutional fields | Confirm covered PHP pathway and reconcile attendance with authorized treatment dates |
| IOP | Hours, attendance, authorized units or days, continued-stay deadlines | Match documented program participation to authorization and payer-specific billing rules |
| Outpatient SUD treatment | Provider credentials, psychotherapy time, same-day services, payer coverage | Match documented service, provider, time, place of service, and payer rules |
| OTP / MOUD | Enrollment, medication pathway, bundles, additional services, payer-specific frequency rules | Confirm whether the program is an OTP or office-based practice and use the applicable payer pathway |
For the detailed technical code differences among SUD treatment settings, use the Substance Abuse Billing Codes reference.
Documentation Must Support Medical Necessity and the Billed Service
An addiction treatment claim should be traceable from the submitted claim back to the assessment, treatment plan, provider, service note, time or unit, authorization, and current level-of-care rationale. Payer requirements differ, but internal consistency between those records is essential.
Pre-Bill Documentation Controls
- The diagnosis and assessment support the treatment plan.
- The service note identifies what was delivered, by whom, when, and for how long when time matters.
- The provider's credential and supervision arrangement meet payer rules.
- The documented level of care matches the authorized and billed service.
- Signatures, credentials, dates, and treatment-plan updates are complete.
- Continued-stay documentation describes the patient's current clinical status rather than simply repeating admission documentation.
Create an exception queue for incomplete or conflicting records. Waiting for the payer to identify documentation problems converts a correctable pre-bill issue into a denial, appeal deadline, and additional staff workload.
UB-04 vs. CMS-1500 in Addiction Treatment Billing
Addiction treatment programs may need institutional claims, professional claims, or both depending on the billing entity, payer contract, treatment setting, and service. The clinical level of care alone does not determine which claim form should be used.
| Claim pathway | Typical role | Key addiction-treatment checks |
|---|---|---|
| UB-04 / 837I | Institutional or facility billing where required by the payer and provider type | Type of bill, revenue codes, procedure codes where required, units, authorization, facility enrollment, dates of service |
| CMS-1500 / 837P | Professional services billed by eligible clinicians or practices | Billing/rendering provider, place of service, CPT/HCPCS, modifiers, diagnosis pointers, authorization, network status |
Some organizations deliver both facility and professional services. Confirm which entity owns each claim and whether the payer permits or requires separate professional billing.
Code-Set Overview for Addiction Treatment Billing
Addiction treatment billing can involve CPT, HCPCS Level II, Medicare-specific G-code pathways, and institutional revenue codes. This page intentionally keeps coding concise so it does not compete with ClaraRCM's dedicated SUD code-reference page.
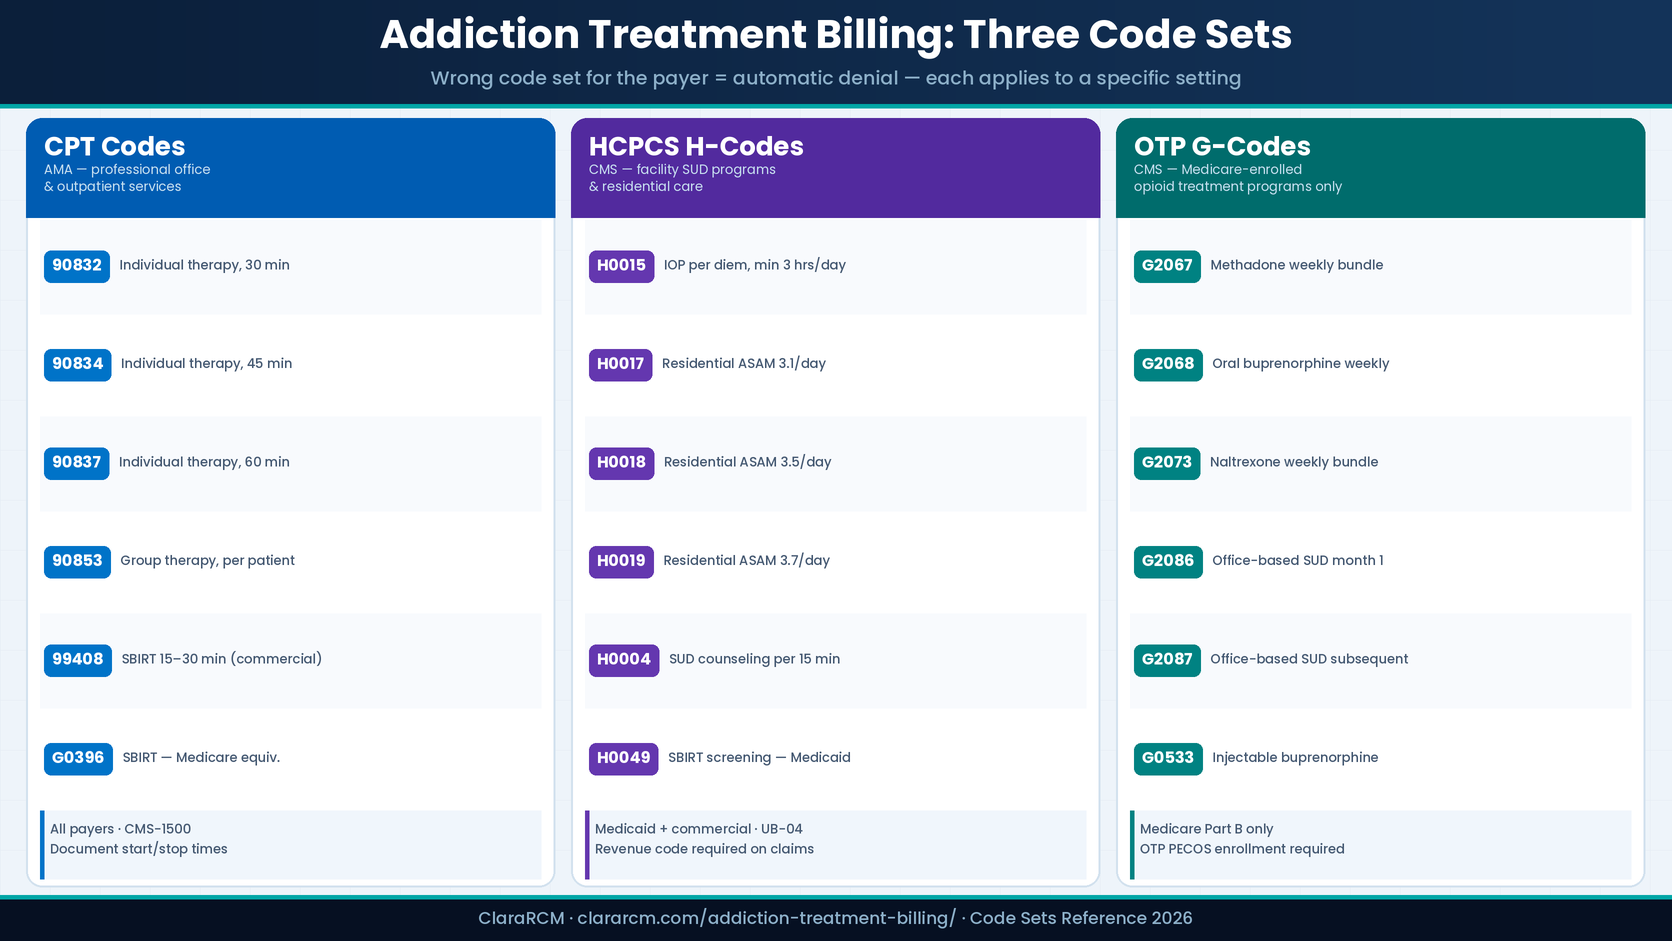
| Code or claim component | Operational use | Verification question |
|---|---|---|
| CPT | Professional evaluation, management, psychotherapy, and other practitioner services | Does the payer cover this service from this provider and setting? |
| HCPCS Level II | Program, behavioral-health, medication, supply, and payer-specific pathways | Which unit, modifier, provider qualification, and coverage rule applies? |
| Medicare SUD / OTP codes | Specific Medicare office-based or OTP treatment pathways | Is the provider enrolled for the pathway and are current CMS requirements met? |
| Revenue codes | Institutional service or accommodation classification | Does the payer require a specific revenue-code and procedure-code combination? |
For detailed H0010-H0019, S0201, H0015, H0018, 0906, 1002, units, modifiers, and level-of-care questions, use our Substance Abuse Billing Codes guide.
How to Bill for Addiction Treatment Services: Seven Steps
To bill addiction treatment services, verify insurance and payer routing, confirm provider and facility eligibility, obtain and track authorization, validate documentation and the payer-approved billing pathway, submit the correct claim, resolve denials by root cause, and reconcile payments and A/R.
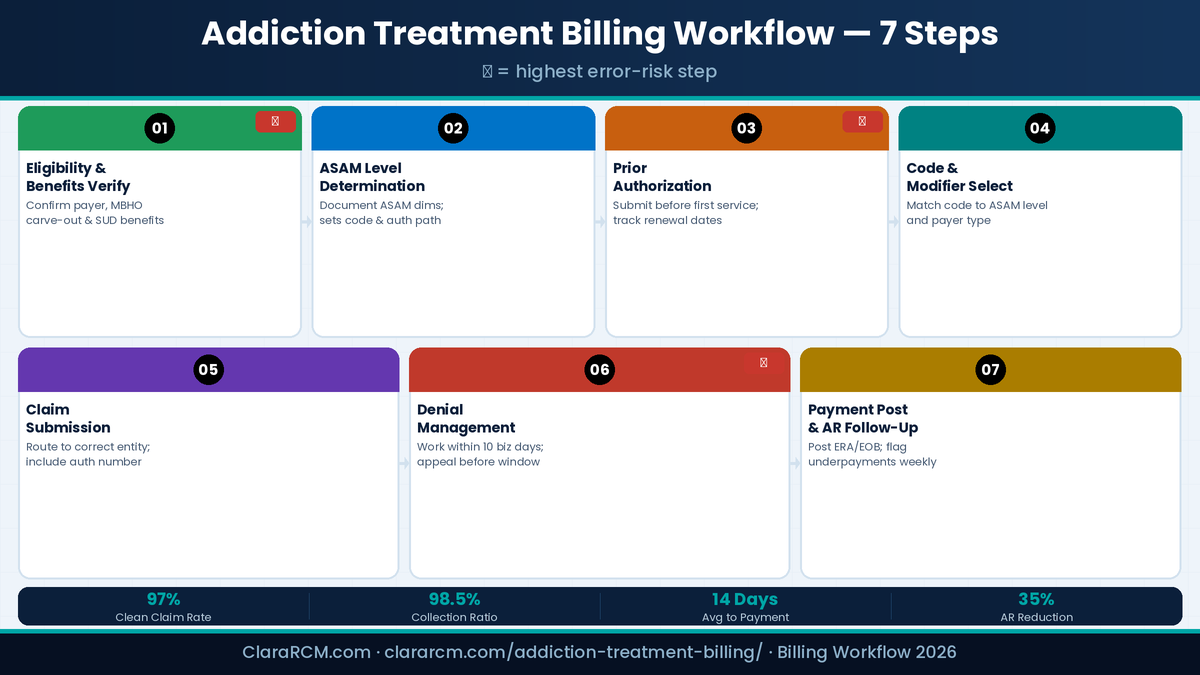
- Verify eligibility, benefits, and payer routing Identify the entity responsible for the SUD benefit, network status, patient responsibility, authorization requirements, claim route, and timely-filing limit.
- Confirm enrollment and credentialing Make sure the facility, billing entity, rendering clinician, and supervision arrangement meet the payer's requirements.
- Obtain and track authorization Record the approved treatment setting, dates, units or days, reference number, and next review deadline.
- Validate documentation and billing pathway Match the actual service, provider, setting, time or unit, authorization, and medical-necessity record to the payer-approved pathway.
- Build and submit the claim Use the correct claim form, payer ID, provider fields, authorization data, modifiers, revenue fields, and other payer-required information.
- Resolve denials by root cause Separate authorization, medical necessity, provider eligibility, payer routing, coding, documentation, and filing problems so the correct team owns the next action.
- Post payments and work A/R Compare remittance to expected reimbursement, investigate underpayments, transfer valid patient responsibility correctly, and follow unresolved balances before deadlines expire.
Common Addiction Treatment Claim Denials and Their Root Causes
The most common addiction treatment claim denials involve authorization, medical necessity, provider eligibility, incorrect payer routing, claim-format or coding mismatches, filing limits, and documentation that does not support the billed service or level of care. The denial message is only the starting point; the billing team should trace each denial back to the operational failure that created it.
1. Authorization Denials
Common causes include missing approval, expired dates, exhausted units, an unapproved level-of-care change, or authorization information that does not match the claim.
2. Medical-Necessity Denials
The payer may determine that submitted documentation does not support the billed treatment setting, continued stay, treatment intensity, or requested service.
3. Provider Eligibility Denials
The facility, clinician, location, taxonomy, or billing entity may not be enrolled, credentialed, contracted, or permitted to bill the service under that arrangement.
4. Wrong Payer or Carve-Out
The claim may have been submitted to the medical plan when the behavioral-health benefit was administered elsewhere, or routed to the wrong payer ID.
5. Claim or Coding Mismatch
Examples include the wrong claim form, unit, modifier, place of service, institutional field, bill type, or payer-specific procedure pathway.
6. Timely-Filing Denials
Front-end rejections, unresolved payer routing, delayed corrected claims, or poor follow-up can consume the filing period before a clean claim reaches the responsible payer.
7. Underpayments and Incorrect Adjustments
A claim can technically pay while still requiring action. Compare the allowed amount, contract, adjustments, and patient responsibility before closing the balance.
8. Duplicate or Overlapping Claims
Resubmissions, overlapping treatment dates, uncorrected frequency conflicts, or incorrect replacement-claim handling can create duplicate edits.
| Denial pattern | What to investigate | Prevention control |
|---|---|---|
| Authorization missing or invalid | Payer, authorized level, dates, units, reference number, level changes | Patient-level authorization ledger reconciled to billed services |
| Medical necessity | Clinical criteria, assessment, treatment plan, current progress, continued-stay support | Clinical review before submission and continued-stay deadlines |
| Provider not eligible | Enrollment, network, credentialing, location, taxonomy, supervision | Payer-specific provider matrix |
| Claim-rule mismatch | Claim form, units, modifiers, place of service, bill type, institutional fields | Payer-specific pre-bill edits |
| Untimely filing | Original submission, rejection history, corrected claims, payer routing | Filing-deadline alerts and rejection work queues |
| Payment variance | Allowed amount, remittance adjustment, contract, patient responsibility | Expected-payment and underpayment review |
Review denial dollars by payer, reason, treatment setting, facility, rendering provider, age, and filing deadline. The highest-frequency denial is not always the largest financial problem.
Repeated denials or aging claims? ClaraRCM's denial management and billing audit and cleanup services review both recovery opportunities and recurring workflow failures.
42 CFR Part 2 Privacy and MHPAEA in Addiction Treatment Billing
SUD billing teams must coordinate payment operations with privacy requirements that apply to substance use disorder records. The updated 42 CFR Part 2 framework permits a single consent for future treatment, payment, and healthcare-operations uses and disclosures when applicable while retaining additional protections for Part 2 records.
Treatment organizations should review consent language, notices, access controls, disclosure workflows, vendor relationships, breach response, and applicable state-law requirements with qualified privacy counsel. See the HHS 42 CFR Part 2 Final Rule fact sheet.
Current MHPAEA Considerations for Addiction Treatment Billing
Mental Health Parity and Addiction Equity Act obligations remain relevant when evaluating coverage limitations affecting mental-health and substance-use-disorder benefits. Treatment centers reviewing a potentially restrictive benefit design should distinguish between the underlying statutory and comparative-analysis obligations and provisions of the 2024 Final Rule that are subject to the federal nonenforcement policy.
The Departments announced in May 2025 that they would not enforce the portions of the 2024 MHPAEA Final Rule that are new relative to the 2013 rule for failures occurring before a final decision in the related litigation, plus an additional 18 months. The underlying MHPAEA statutory obligations, including amendments made by the Consolidated Appropriations Act, 2021, remain in effect. :contentReference[oaicite:2]{index=2}
For case-specific parity questions, review the current plan terms, applicable statute and regulations, comparative-analysis requirements, current federal guidance, state requirements, and available appeal rights rather than relying on a generalized claim that 2026 automatically created a new enforcement standard.
Compliance note: Privacy, parity, state insurance, licensure, and payer-contract requirements are fact specific. This guide is not legal advice. Consult qualified counsel and applicable regulators before changing policy or filing a legal or parity-based appeal.
Payment Posting, Underpayments, and Addiction Treatment A/R
A claim is not finished when money arrives; it is finished when the remittance is reconciled and every remaining balance has a valid owner and next action. Automated payment posting can improve speed, but it should not automatically close claims that paid below expectation or shifted responsibility incorrectly.
Payment-Posting Controls
- Reconcile electronic remittance and deposit totals.
- Compare allowed and paid amounts to the applicable contract or documented reimbursement expectation.
- Review adjustment and remark codes before writing off balances.
- Separate legitimate patient responsibility from payer processing errors.
- Route underpayments, recoupments, and coordination-of-benefits issues to dedicated queues.
A/R Segmentation That Drives Action
Segment addiction-treatment A/R by payer, age, balance, denial category, authorization status, treatment setting, filing deadline, and appeal deadline. A smaller balance with an expiring appeal right may require action before a larger claim that remains within a normal payer cycle.
ClaraRCM provides payment posting services and A/R follow-up as connected revenue-cycle functions.
Addiction RCM vs. Addiction Treatment Billing
Addiction RCM is broader than claim submission. Addiction treatment billing focuses on creating, submitting, correcting, and following claims, while addiction treatment revenue cycle management coordinates the financial workflow from intake and eligibility through authorization, claims, denials, payments, underpayments, and final A/R resolution.
| Function | Billing-only scope | Full addiction RCM scope |
|---|---|---|
| Eligibility and payer routing | May rely on information supplied by the treatment center | Verification incorporated into the pre-bill process |
| Credentialing | Often excluded | Provider and facility participation monitored |
| Authorization | Often excluded or limited | Approved dates, units, levels, and continued-stay deadlines reconciled with claims |
| Claim production | Core function | Connected with payer, authorization, provider, and documentation controls |
| Denials | Correction and resubmission may be limited | Root-cause analysis, appeals, recovery, and prevention |
| Payments | Posting may be included | Posting plus contract and underpayment variance review |
| A/R | May be limited by age or claim type | Prioritized by value, cause, payer, age, and deadline |
| Reporting | Submission and claim-status metrics | Financial and operational KPIs across the full revenue cycle |
Third-Party Billing for Substance Abuse Treatment Programs
Third-party billing means assigning some or all addiction-treatment revenue-cycle functions to an outside organization. The contract should clearly identify who owns insurance verification, authorizations, coding review, claims, denials, appeals, payment posting, patient balances, old A/R, reporting, escalation, security, and termination support.
When Should a Treatment Center Consider Outsourcing Billing?
Outsourcing becomes more useful when internal teams cannot consistently maintain payer-specific insurance verification, authorization deadlines, claim production, denial follow-up, payment reconciliation, and A/R across multiple treatment settings or payer contracts.
Common signs include:
- Authorizations or continued-stay reviews frequently lapse.
- The same denial causes appear month after month.
- A/R over 90 days is growing.
- Rejected claims remain unresolved long enough to threaten filing limits.
- Payment posting does not include underpayment review.
- Staff turnover disrupts payer-specific knowledge.
- Leadership lacks reporting by payer, denial reason, level of care, and A/R age.
In-House vs. Outsourced Addiction Treatment Billing
| Consideration | In-house billing | Outsourced billing |
|---|---|---|
| Operational control | Direct internal management | Requires clearly defined vendor accountability and communication |
| Payer expertise | Depends on recruitment, training, and staff retention | Should provide specialty and payer-specific expertise |
| Coverage | Can be vulnerable to turnover, leave, and staffing shortages | May offer broader team coverage |
| Cost structure | Salary, benefits, management, software, clearinghouse, training | Contracted fee plus any excluded or additional services |
| Best fit | Organizations with sufficient volume and experienced internal revenue-cycle leadership | Programs needing specialized capacity, workflow cleanup, denial recovery, or broader RCM coverage |
A percentage fee is not comparable until the included scope is comparable. Ask who verifies benefits, tracks authorization, maintains payer rules, follows rejections, works appeals, identifies underpayments, handles older A/R, and reports performance.
For outsourced support, see ClaraRCM's Substance Abuse Billing Services.
Related ClaraRCM Resources
Addiction Treatment Billing Performance Estimator
Estimate current collections, uncollected charges, and initially denied charges using your own monthly figures. This is a screening tool—not a prediction of recoverable revenue.
Request a free billing audit to review payer routing, authorization, denial, payment, and A/R workflows. Your estimate: -
Request received—thank you.
ClaraRCM will review your information and follow up about the billing audit.
Book a 30-Minute CallFrequently Asked Questions About Addiction Treatment Billing
How does addiction treatment billing work?
Addiction treatment billing begins by verifying insurance, the responsible behavioral-health payer, network status, and authorization requirements. The treatment center then confirms provider eligibility, documents the service and level of care, selects the payer-approved claim pathway, submits the claim, resolves rejections or denials, posts the remittance, and follows all remaining payer or patient balances.
How does addiction insurance billing work?
Addiction insurance billing starts by confirming active SUD benefits, the responsible behavioral-health administrator, network participation, patient responsibility, authorization requirements, level-of-care coverage, payer ID, and claim route. The billing team then submits the claim according to the payer's professional or institutional requirements and follows it through payment or denial resolution.
How does addiction Medicaid billing differ?
Addiction Medicaid billing varies by state and managed-care plan. Treatment centers should verify program enrollment, covered treatment settings, accepted CPT or HCPCS codes, units, modifiers, authorization requirements, claim routing, filing limits, and appeal rules using the current state Medicaid and managed-care instructions.
What are common addiction treatment claim denials?
Common addiction treatment claim denials involve missing or expired authorization, documentation that does not support the billed level of care, facility or clinician eligibility problems, incorrect payer routing, claim-form or code mismatches, timely-filing failures, duplicate claims, and underpayments or adjustments that require review.
How should treatment centers manage prior authorization?
Track authorization at the patient level, including the approved treatment setting, dates, days or units, reference number, review deadline, and payer response. Reconcile the authorization whenever the patient's level of care changes and before final claim release.
What should be verified before admitting an insured patient?
Verify active coverage, the entity administering SUD benefits, facility and clinician network status where applicable, patient responsibility, the covered level of care, prior-authorization requirements, utilization-review instructions, claim route, payer ID, and filing limits. Document the source and date of verification.
Does addiction treatment use UB-04 or CMS-1500 claims?
It can use either depending on the payer, provider type, contract, and service. Institutional or facility services may use UB-04 or 837I claims, while eligible professional services may use CMS-1500 or 837P claims. The treatment level alone does not determine the claim form.
What is the difference between addiction treatment billing and addiction RCM?
Addiction treatment billing focuses on claim preparation, submission, correction, and follow-up. Addiction RCM also coordinates insurance verification, payer routing, credentialing, authorization, documentation controls, denial prevention, appeals, payment variance review, A/R recovery, and financial reporting.
What is third-party billing for substance abuse treatment?
Third-party billing means assigning some or all addiction-treatment billing or revenue-cycle functions to an outside company. The agreement should clearly define responsibility for eligibility, authorization, claims, denials, appeals, payment posting, A/R, reporting, data access, security, and escalation.
When should a treatment center consider outsourcing billing?
Outsourcing may be appropriate when internal teams cannot consistently manage payer routing, authorization deadlines, claim production, denial appeals, underpayment review, or aging A/R, or when staff turnover and payer complexity make specialty expertise difficult to maintain.
Where should I look up substance abuse billing codes?
Use the current official code set together with the responsible payer's provider manual, fee schedule, contract, and claim instructions. ClaraRCM maintains a separate Substance Abuse Billing Codes guide covering CPT, HCPCS, H-codes, S-codes, revenue codes, and common treatment-setting questions.

Andleeb Asghar, Licensed Pharmacist
RCM Specialist & Founder , ClaraRCM
Andleeb Asghar is a pharmacist, medical billing professional, and revenue cycle management specialist with experience supporting U.S. billing operations, substance use disorder revenue-cycle workflows, payer-specific billing, denial management, and end-to-end RCM.
Last updated: September 15, 2026. ClaraRCM provides medical billing and revenue cycle management support. This article is educational and is not legal, clinical, coding, reimbursement, or payer-contract advice. Coverage, authorization, coding, privacy, enrollment, claim-form, and reimbursement requirements vary by payer, contract, state, provider type, treatment setting, and date of service. Verify current requirements with official code sets, applicable regulators, current payer materials, contracts, and qualified professional advisers.