Substance Abuse Billing Codes: CPT, HCPCS, H-Codes, and Revenue Codes (2026)
Substance abuse billing codes come from several coding systems rather than one universal SUD code list. Professional evaluation and therapy services commonly use CPT codes; program services may use HCPCS H-codes or S-codes; Medicare has specific G-code pathways for office-based SUD treatment and opioid treatment programs; and institutional claims can require revenue codes. The correct combination depends on the service actually delivered, unit, provider, treatment setting, payer, state requirements, contract, claim format, and current billing instructions.

This page is intentionally a technical code-reference resource. It explains commonly searched substance abuse billing CPT codes, HCPCS codes, H-codes, S-codes, Medicare G-codes, and revenue codes while showing which facts must be verified before a claim is built.
Searchers often use the phrase “substance abuse billing CPT codes,” but SUD billing does not rely on CPT alone. Depending on the treatment setting and payer, the claim may involve CPT, HCPCS Level II, revenue codes, or a combination of these systems.
For the operational revenue-cycle process—eligibility, benefit carve-outs, authorization, claim routing, denials, payment posting, and A/R—use our separate addiction treatment billing workflow guide. For outsourced billing support, visit our substance abuse billing services page.
Common Substance Abuse Billing Codes: Quick Reference
The table below is a starting reference, not a payer crosswalk. It groups commonly searched SUD billing codes by their general use. Before billing, verify the current descriptor, treatment setting, provider eligibility, unit, authorization, claim format, modifier, revenue code, and payer-specific policy.
| Code | Common billing context | Code type | Key verification |
|---|---|---|---|
| 90791 / 90792 | Psychiatric diagnostic evaluation | CPT | Provider type, frequency, payer rules |
| 90832 / 90834 / 90837 | Individual psychotherapy | CPT | Documented psychotherapy time and payer edits |
| 90853 | Group psychotherapy | CPT | Group documentation and coverage |
| H0001 | Alcohol and/or drug assessment | HCPCS Level II | State/payer coverage and unit |
| H0004 | Behavioral-health counseling and therapy | HCPCS Level II | Provider, unit, modifier, payer limits |
| H0005 | Alcohol and/or drug group counseling | HCPCS Level II | Do not assume equivalence with CPT 90853 |
| H0010-H0014 | Detoxification and withdrawal-management services | HCPCS Level II | Setting, acuity, unit, contract |
| H0015 | Alcohol/drug intensive outpatient program | HCPCS Level II | Program requirements, payer mapping, revenue code |
| H0017-H0019 | Residential behavioral-health treatment categories | HCPCS Level II | Facility type, local crosswalk, included services |
| S0201 | Partial hospitalization services, less than 24 hours | HCPCS Level II | Payer recognition and claim methodology |
| S9480 | Psychiatric intensive outpatient services | HCPCS Level II | Psychiatric versus SUD program pathway |
| H2036 | Alcohol/drug treatment program, per diem | HCPCS Level II | State/payer level-of-care mapping |
| 0906 | Intensive outpatient services – chemical dependency | Revenue code | Institutional claim and payer-required pairing |
| 1002 | Residential treatment – chemical dependency | Revenue code | Accommodation billing, bill type, contract, payer policy |
Important: A valid code does not independently establish coverage or payment. Coverage still depends on the patient's benefit, provider/program eligibility, medical necessity where applicable, authorization, documentation, contract, units, and the payer's current billing instructions.
How to Select a Substance Abuse Billing Code Family
Start with the service—not the keyword, diagnosis, or program name. Identify who performed the service, what was delivered, where it occurred, how time or units were documented, which payer is responsible, and whether the claim is professional or institutional. Only then should the team select the code and related claim elements.
| Code family | Common purpose | Common claim context | Verify before use |
|---|---|---|---|
| CPT | Psychotherapy, diagnostic evaluation, E/M, and certain SBIRT services | Usually professional claims | Current CPT definition, time rule, provider eligibility, payer coverage and edits |
| HCPCS H-codes | Behavioral health and SUD assessment, counseling, detox, IOP, residential, and support services | Professional or institutional depending on payer/program | State Medicaid manual, managed-care contract, unit, modifier, provider and place of service |
| HCPCS S-codes | Temporary/non-Medicare service codes including certain IOP and PHP pathways | Often commercial or payer-specific | Whether the responsible payer recognizes the S-code |
| HCPCS G-codes | Medicare SBIRT, office-based SUD bundles, and Medicare OTP services | Medicare-specific pathways | Enrollment, practitioner/site eligibility, time, frequency, bundle and add-on rules |
| Revenue codes | Institutional service or accommodation classification | UB-04/837I line item | Revenue-code definition, bill type, facility eligibility and payer-specific HCPCS/CPT pairing |
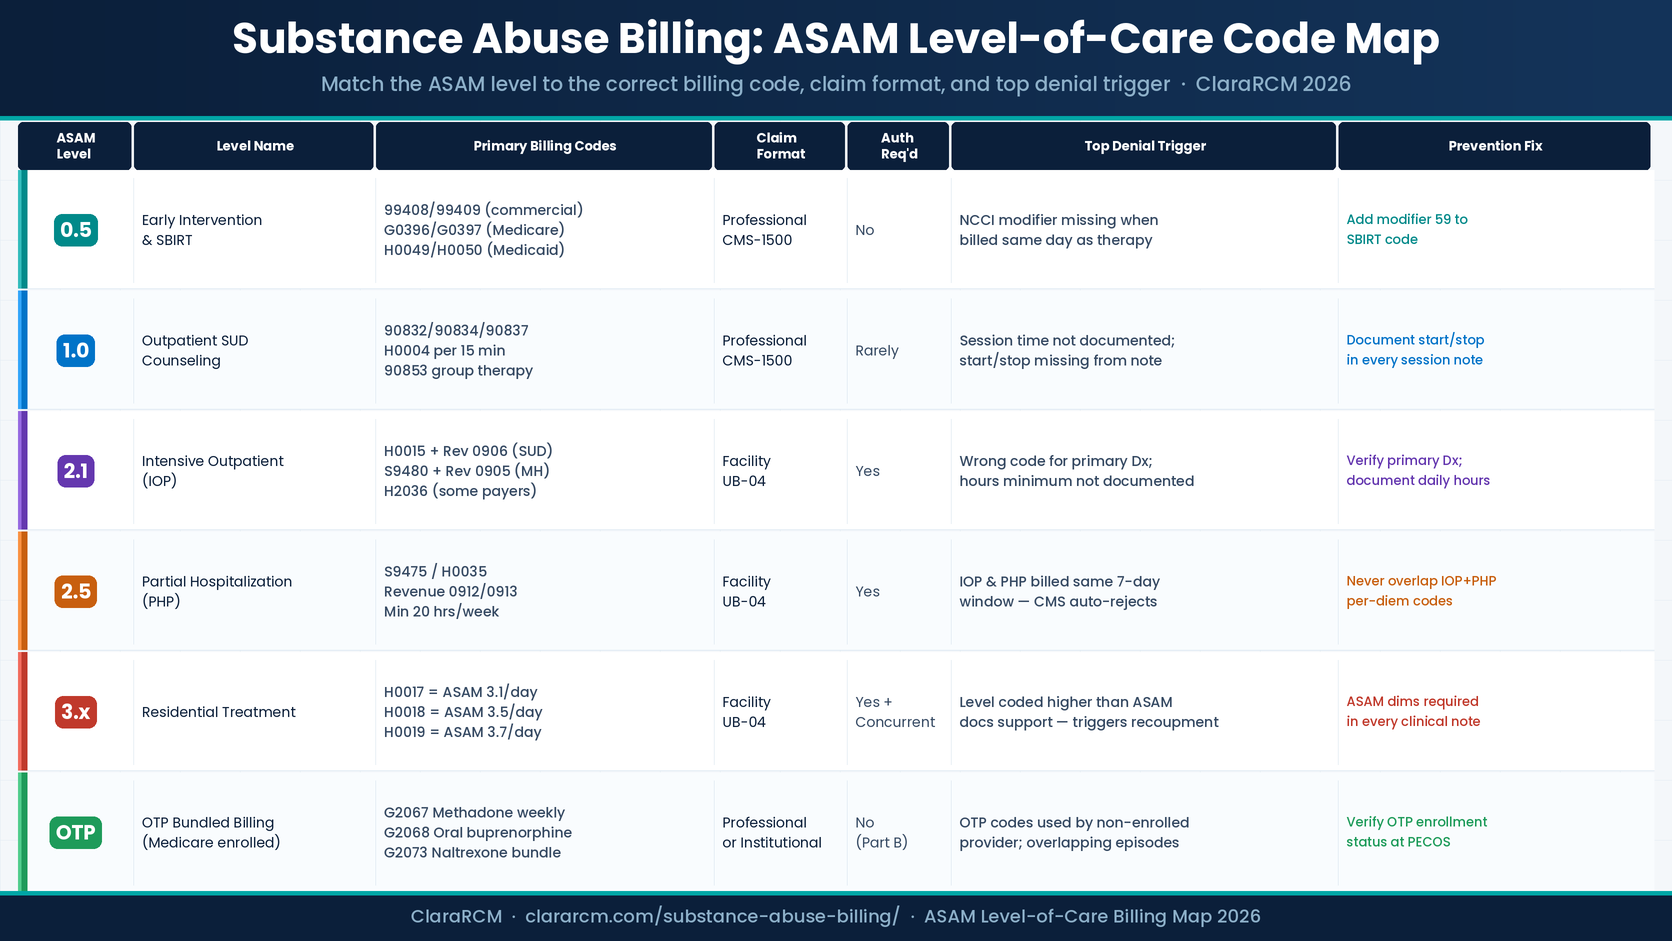
No national crosswalk makes an ASAM level automatically equal one HCPCS code. ASAM supports the clinical level-of-care determination; the payer contract, state program, and billing manual determine how the service is reported.
SUD Code-Family Starting Point
Select the service and payer. This tool identifies a code family to investigate; it does not select or authorize a billable code.
Substance Abuse CPT Codes and SBIRT Codes
Substance abuse CPT codes are generally the same professional procedure codes used for psychotherapy, psychiatric evaluation, and other covered professional services. An SUD diagnosis does not create a separate psychotherapy code family. Code selection must reflect the documented service and, when applicable, the required time threshold.
| Code | Plain-language use | Unit/time | Key check |
|---|---|---|---|
| 90791 / 90792 | Psychiatric diagnostic evaluation; 90792 includes medical services | Per encounter under current CPT rules | Provider type, payer frequency, complete diagnostic record |
| 90832 / 90834 / 90837 | Individual psychotherapy at different time levels | Time-based | Document actual psychotherapy time and apply current CPT time rules |
| 90853 | Group psychotherapy | Per patient/session under applicable rules | Group documentation, provider eligibility and payer limits |
| 99408 / 99409 | Structured alcohol/substance-use screening and brief intervention when recognized by the payer | Time-based | Current CPT definition, coverage and same-day edits |
| G2011 | Medicare structured assessment and brief intervention, 5-14 minutes | Time-based | Medicare documentation and coverage requirements |
| G0396 / G0397 | Medicare structured assessment and brief intervention at longer time levels | Time-based | Documented time and medical-record support |
| H0049 / H0050 | Screening / brief intervention codes used by some Medicaid programs | Payer/state defined | State Medicaid policy determines whether these codes are covered |
Medicare source: CMS describes Medicare SBIRT pathways and documentation requirements in its SBIRT Services guidance. Always confirm current Medicare and payer instructions for the date of service.
HCPCS H-Codes for Substance Abuse Billing
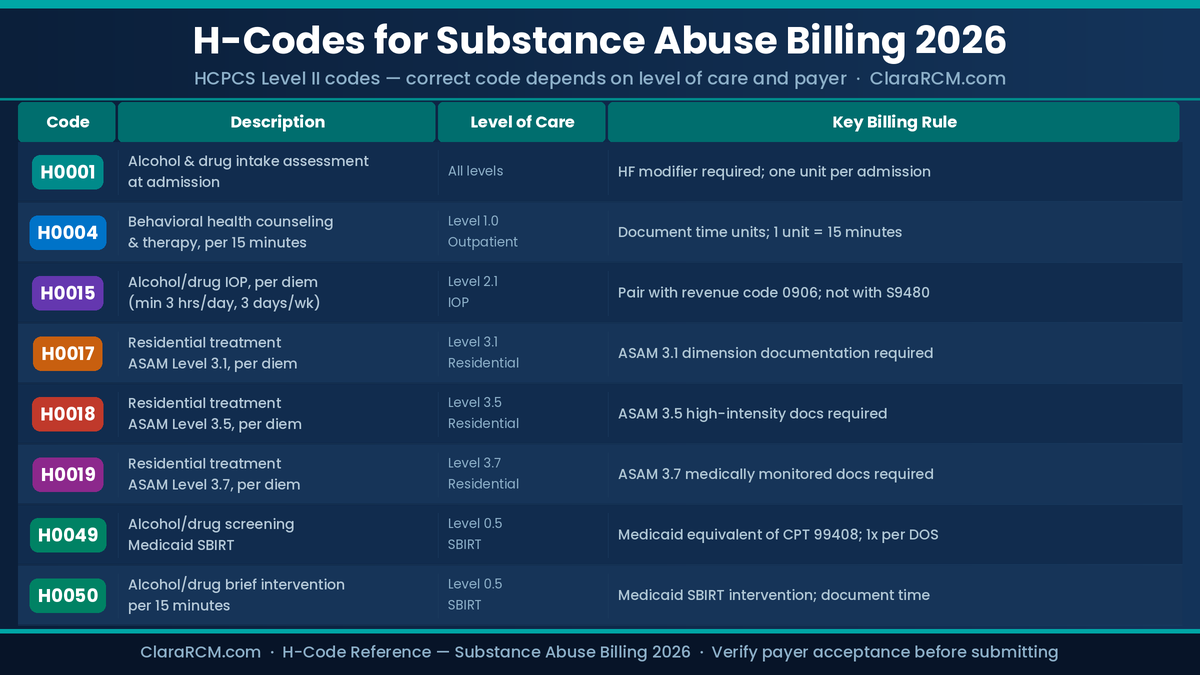
HCPCS H-codes describe behavioral-health and substance-use services commonly administered through Medicaid, managed-care plans, and program contracts. The descriptor identifies a service category; it does not by itself guarantee coverage, establish provider eligibility, create a universal ASAM mapping, or determine the claim form every payer requires.
| Code | Service category | Common unit/context | Do not assume |
|---|---|---|---|
| H0001 | Alcohol and/or drug assessment | Assessment/encounter | Automatic one-time coverage or a universal modifier |
| H0004 | Behavioral-health counseling and therapy | 15-minute unit in the national descriptor | Every payer allows the same provider types or unit limits |
| H0005 | Alcohol and/or drug group counseling by a clinician | Payer-defined session/unit rules | That it is interchangeable with CPT 90853 |
| H0010-H0014 | Detoxification and withdrawal-management services | Setting-specific services | That one code fits every inpatient, residential, or ambulatory setting |
| H0015 | Alcohol/drug intensive outpatient program | Program service | Universal pairing with revenue code 0906 |
| H0017-H0019 | Residential behavioral-health program categories | Per diem | A universal H-code-to-ASAM crosswalk |
| H0020 | Alcohol/drug service involving methadone administration and/or service | Payer-defined | That it replaces Medicare OTP weekly G-code bundles |
| H0035 | Mental-health partial hospitalization, less than 24 hours | Per diem | Automatic acceptance for SUD PHP |
| H0038 | Self-help/peer services | 15-minute unit in the national descriptor | Coverage without confirming provider qualification requirements |
| H2034-H2036 | Halfway-house or alcohol/drug treatment-program services | Varies by code; H2036 is per diem | The same level-of-care mapping in every state |
H0010-H0014 Detox and Withdrawal-Management Billing Codes
The H0010-H0014 family differentiates detoxification services by setting and level of medical intensity. These are HCPCS Level II codes—not CPT codes—and a payer's manual determines whether the code is covered, which provider or facility may report it, how authorization works, and which units or claim format apply.
| Code | National descriptor, summarized | Setting cue | Verification point |
|---|---|---|---|
| H0010 | Sub-acute alcohol/drug detoxification | Residential addiction program, inpatient | Acuity, authorization, facility/program eligibility and payer contract |
| H0011 | Acute alcohol/drug detoxification | Residential addiction program, inpatient | Medical intensity and payer requirements |
| H0012 | Sub-acute detoxification | Residential addiction program, outpatient designation in descriptor | Exact payer interpretation, eligibility and place of service |
| H0013 | Acute detoxification | Residential addiction program, outpatient designation in descriptor | Exact payer interpretation, acuity and program eligibility |
| H0014 | Ambulatory detoxification | Ambulatory/non-residential | Payer unit, provider requirements and medication rules |
What Is H0010?
H0010 is an HCPCS Level II code for sub-acute alcohol and/or drug detoxification in a residential addiction-treatment program. It is not a CPT code. The code describes the service category, but billing still depends on the facility or program's eligibility, authorization, contract, covered unit, claim format, and the responsible payer's current instructions.
Is H0010 a CPT Code?
No. H0010 is an HCPCS Level II code. Users often search for “CPT code H0010” or “H0010 CPT code,” but CPT and HCPCS Level II are different coding systems. Preserving that distinction is important when reviewing payer manuals and fee schedules.
What Is H0014?
H0014 describes ambulatory alcohol and/or drug detoxification services. Unlike H0010, which points to a residential sub-acute detox setting, H0014 points to an ambulatory detoxification pathway. The payer may impose specific provider, medication, observation, unit, documentation, and authorization requirements.
H0010 vs. H0014
| Question | H0010 | H0014 |
|---|---|---|
| Code system | HCPCS Level II | HCPCS Level II |
| General setting cue | Residential sub-acute detoxification | Ambulatory detoxification |
| Primary distinction | Residential program pathway | Ambulatory/non-residential pathway |
| Must verify | Facility, acuity, authorization, unit and payer rules | Provider, medication, unit, documentation and payer rules |
Do not call H0010-H0014 CPT codes. They are HCPCS Level II codes. The article can answer “CPT code for detox” search intent while still using technically correct terminology.
S0201 Billing Code for Partial Hospitalization
S0201 is an HCPCS Level II S-code for partial hospitalization services lasting less than 24 hours and described on a per-diem basis. It is not a CPT code. Recognition varies by payer, so S0201 should not automatically be substituted for H0035, S9475, or a payer-specific institutional PHP methodology.
What Is S0201?
S0201 identifies a partial-hospitalization service category of less than 24 hours. The code itself does not establish whether a particular plan covers the program, which diagnoses qualify, what services are included in the per diem, or whether an institutional revenue code is also required.
Is S0201 a CPT Code?
No. S0201 is an HCPCS Level II S-code. S-codes are generally used in non-Medicare or payer-specific billing arrangements. A treatment provider should verify that the patient's payer recognizes S0201 before building the claim around it.
S0201 vs. H0035 vs. S9475
| Code | Descriptor, summarized | What the wording emphasizes | Before billing |
|---|---|---|---|
| S0201 | Partial hospitalization services, less than 24 hours | General PHP service | Confirm payer recognition and institutional/professional instructions |
| H0035 | Mental-health partial hospitalization, less than 24 hours | Mental-health PHP | Confirm whether the payer uses it for the relevant program and benefit |
| S9475 | Ambulatory substance-abuse treatment or detoxification, per diem | SUD-specific ambulatory program | Confirm covered service, included components and claim requirements |
Does Medicare Use S0201?
Do not assume the commercial S0201 pathway applies to traditional Medicare. Medicare PHP and IOP services follow Medicare's own eligible-setting, certification, HCPCS, revenue-code, condition-code, and payment requirements. Verify the Medicare pathway that applies to the provider and service rather than carrying an S-code assumption into Medicare billing.
H0015 Billing Guidelines for Substance Abuse IOP
H0015 is an HCPCS Level II code for an alcohol and/or drug intensive outpatient treatment program. Its national descriptor identifies an intensive program built around an individualized treatment plan and specified program intensity, but the code does not create a universal payment amount, ASAM mapping, revenue-code pairing, or claim methodology.
What Is H0015?
H0015 describes an intensive outpatient alcohol/drug treatment program that includes structured therapeutic services such as assessment, counseling, crisis intervention, and treatment-related activities or education. Providers should confirm that the actual program meets the code definition and the responsible payer's program requirements.
Is H0015 a CPT Code?
No. H0015 is an HCPCS Level II code. It is commonly searched as “H0015 CPT code,” but using the correct HCPCS terminology makes it easier to find the applicable state Medicaid, managed-care, or commercial payer policy.
What Is the Billing Unit for H0015?
Do not assume that every payer applies H0015 in exactly the same billing configuration. The national descriptor defines the intensive outpatient program service, while payer manuals and contracts determine claim configuration, authorization, covered days or units, included services, reimbursement methodology, and any required institutional pairing.
Does H0015 Require Revenue Code 0906?
Not universally. Revenue code 0906 identifies intensive outpatient services for chemical dependency on institutional claims, so some payer arrangements may use 0906 with an appropriate SUD IOP procedure code. However, the H0015/0906 combination should never be assumed across all commercial plans, Medicaid programs, facilities, and claim types.
H0015 vs. S9480 vs. H2036
| Code | Service focus | General billing context | High-risk assumption to avoid |
|---|---|---|---|
| H0015 | Alcohol/drug intensive outpatient program | SUD IOP pathway | Assuming every payer pairs H0015 with revenue code 0906 |
| S9480 | Intensive outpatient psychiatric services | Psychiatric IOP pathway | Using a psychiatric code solely because the patient has a co-occurring diagnosis |
| H2036 | Alcohol/drug treatment program | Broad program per-diem pathway | Copying one state's level-of-care mapping into another state or contract |
How Does Medicare IOP Billing Differ?
Traditional Medicare has a separate IOP benefit and billing structure. Applicable hospital, critical access hospital, community mental health center, FQHC, and RHC pathways follow CMS requirements rather than simply defaulting to H0015.
CMS requires Condition Code 92 for applicable IOP claims and applies setting-specific billing instructions. Medicare's IOP pathway therefore should not be reduced to a commercial H0015/S9480 comparison.
Medicare source: Review current CMS IOP requirements through CMS Condition Code 92 guidance and the applicable Medicare Claims Processing Manual instructions.
Residential Substance Abuse Billing Codes: H0017, H0018, H0019, and H2036
Residential code selection must follow the actual code descriptor and the payer's contracted level-of-care methodology. The national H-code labels distinguish hospital versus non-hospital residential categories and short-term versus long-term categories. They do not create a universal rule that H0017, H0018, or H0019 automatically equals one specific ASAM level.
| Code | Descriptor, summarized | Unit | Required local check |
|---|---|---|---|
| H0017 | Hospital residential behavioral-health program, without room and board | Per diem | Payer level-of-care mapping and facility eligibility |
| H0018 | Short-term non-hospital residential behavioral-health program, without room and board | Per diem | Definition of short term, covered program, included services and authorization |
| H0019 | Long-term non-medical, non-acute residential behavioral-health program, without room and board | Per diem | Length/level definition, provider eligibility and contract exclusions |
| H2036 | Alcohol/drug treatment program | Per diem | State/payer mapping, program requirements and modifier |
H0018 Billing Guidelines
H0018 is an HCPCS Level II code for short-term residential behavioral-health treatment in a non-hospital residential treatment program, without room and board, billed per diem. The descriptor identifies the service category but does not establish a universal residential benefit, ASAM level, authorization rule, or reimbursement method.
Is H0018 Inpatient or Residential?
H0018 describes a non-hospital residential treatment program. “Residential” and “hospital inpatient” should not be treated as interchangeable billing concepts. The provider should confirm the licensed program type, payer contract, bill type or claim format, authorization, and eligibility requirements that apply to the residential service.
Does H0018 Include Room and Board?
No—the H0018 descriptor states “without room and board.” If accommodation or room-and-board charges are separately reportable under the applicable payer arrangement, the responsible contract or institutional billing policy determines how those charges are represented.
H0018 vs. H0019
| Question | H0018 | H0019 |
|---|---|---|
| Residential category | Short-term non-hospital residential treatment | Long-term non-medical, non-acute residential treatment |
| Unit | Per diem | Per diem |
| Room and board in descriptor | Without room and board | Without room and board |
| Final determination | Payer/state contract and program requirements | Payer/state contract and program requirements |
Does H0018 Equal ASAM 3.5?
Not as a universal national billing rule. A state Medicaid program, managed-care plan, or commercial payer may publish its own crosswalk connecting H0018 with a defined level of care, but providers should not copy that mapping into another payer or state without verification.
Running a residential, IOP, PHP, or outpatient treatment program? If recurring claims are denying because of code selection, authorization, payer routing, units, facility billing, or unpaid balances, see ClaraRCM's substance abuse billing services.
How ASAM Criteria Relate to Billing Code Selection
ASAM Criteria support clinical level-of-care determination and medical-necessity documentation; they do not replace the payer's billing manual. The defensible workflow is to document the assessed needs and delivered level of care, then use the responsible payer's current crosswalk or contract to identify the covered code, unit, claim form, revenue code, modifier, authorization, and provider requirements.
- Document the clinical assessment and level of care. The record should support what was medically necessary and actually delivered.
- Identify the responsible payer and benefit administrator. Include behavioral-health carve-outs and managed-care organizations where applicable.
- Open the current provider manual, contract and fee schedule. Confirm the covered code and unit for the date of service.
- Confirm provider and program eligibility. A technically valid code can still deny when the facility, program or rendering professional is not eligible.
- Match the remaining claim elements. Claim form, bill type, revenue code, modifier, diagnosis pointers, units and authorization must align.
Clinical-policy source: Use the ASAM payment and policy resources alongside the applicable payer's current billing instructions.
Medicare SUD, Office-Based, and OTP Billing Codes
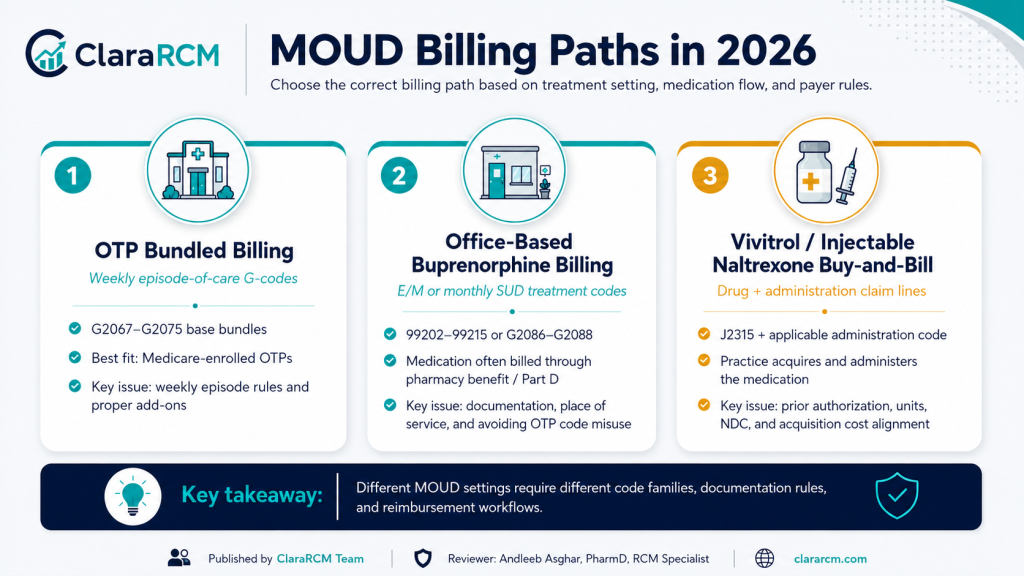
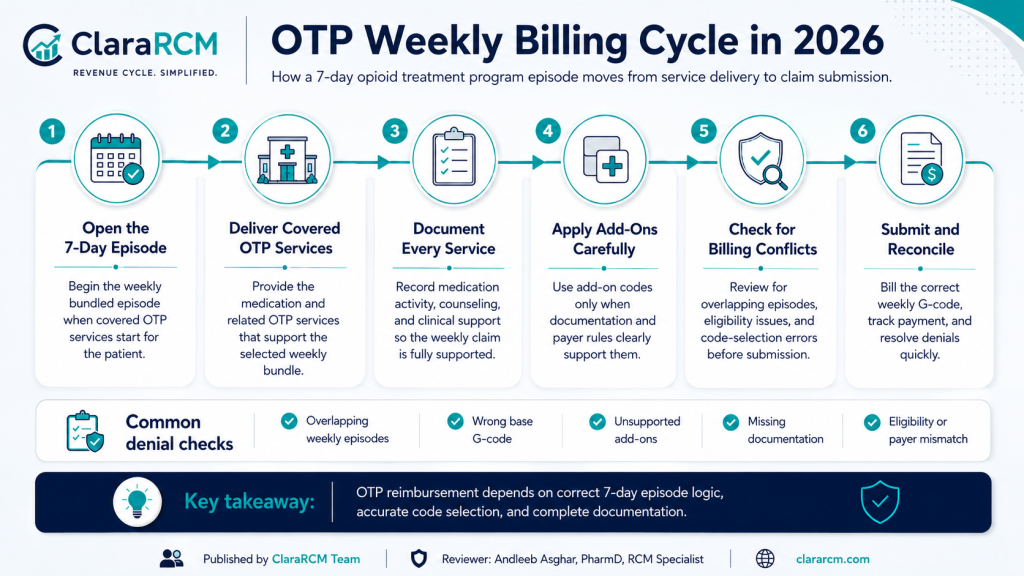
Medicare separates office-based SUD treatment from services billed by Medicare-enrolled opioid treatment programs. Physicians and eligible non-physician practitioners may use G2086-G2088 for qualifying monthly office-based SUD treatment, while Medicare-enrolled OTPs use specific base bundles and add-on codes.
| Code/group | Medicare pathway | Frequency/context | Critical rule |
|---|---|---|---|
| G2086 | Office-based SUD treatment | First calendar month | Includes treatment-plan development, care coordination and required qualifying service time |
| G2087 | Office-based SUD treatment | Subsequent calendar month | Meet CMS service and time requirements |
| G2088 | Additional office-based SUD treatment work | Additional qualifying time | Use with the applicable primary office-based SUD treatment pathway |
| G2067 | OTP methadone bundle | Seven-day episode | Provision by a Medicare-enrolled OTP |
| G2068 | OTP oral buprenorphine bundle | Seven-day episode | Follow current CMS frequency and episode rules |
| G2069 | OTP injectable buprenorphine bundle | CMS-defined episode/frequency | Verify current medication and frequency instructions |
| G2073 | OTP naltrexone bundle | Weekly episode pathway | Provision by a Medicare-enrolled OTP |
| G2074 / G2075 | Other OTP base-bundle pathways | Weekly episode | Use only when the specific CMS descriptor applies |
| G0533 | Weekly injectable buprenorphine OTP bundle | Seven-day episode | Follow current CMS drug and frequency requirements |
| G2076-G2080 | Selected OTP intake, assessment, take-home, counseling or related add-ons | Code-specific | Use only when current CMS add-on requirements are met |
| G0137 | OTP intensive outpatient services add-on | Seven-contiguous-day episode | CMS requires the applicable IOP service-intensity requirements |
| G0532 / G0534-G0536 / G1028 | Additional OTP add-on pathways | Code-specific | Verify current CMS frequency, service and documentation requirements |
Medicare sources: CMS maintains office-based SUD treatment billing guidance, OTP billing instructions, and current OTP payment tables.
Need operational support with MOUD or OTP claims? For weekly bundles, office-based SUD treatment, medication pathways, denials, and A/R, see ClaraRCM's substance abuse billing services.
Substance Abuse and Behavioral Health Revenue Codes
A revenue code classifies an institutional accommodation, department, or service line; it does not automatically replace the related HCPCS or CPT code. On UB-04/837I claims, the payer may require specific combinations of revenue code, procedure code, units, bill type, authorization, and facility eligibility.
| Revenue code | Category | Potential billing context | Required check |
|---|---|---|---|
| 0905 | Intensive outpatient services – psychiatric | Psychiatric IOP institutional claims | Provider type, bill type, procedure code and payer requirements |
| 0906 | Intensive outpatient services – chemical dependency | SUD/chemical-dependency IOP institutional claims | Do not assume universal pairing with H0015 |
| 0912 | Partial hospitalization – less intensive | Behavioral-health PHP institutional claims where applicable | Payer and facility billing instructions |
| 0913 | Partial hospitalization – intensive | Behavioral-health PHP institutional claims where applicable | Payer and facility billing instructions |
| 1001 | Residential treatment – psychiatric | Behavioral-health accommodation | Bill type, facility classification and payer rules |
| 1002 | Residential treatment – chemical dependency | Chemical-dependency residential accommodation | Bill type, facility eligibility, contract and payer instructions |
What Is Revenue Code 0906?
Revenue code 0906 identifies intensive outpatient services for chemical dependency. It may appear on institutional SUD IOP claims, but the revenue code alone does not identify every required claim element. Confirm the procedure code, units, bill type, authorization, provider/facility eligibility, and payer-specific pairing.
Does H0015 Always Use Revenue Code 0906?
No. H0015 and 0906 are logically related to SUD IOP billing, but there is no universal rule requiring the same H0015/0906 combination for every payer, state Medicaid program, facility, or contract.
Revenue Code 1002 for Substance Abuse Residential Treatment
Revenue code 1002 identifies behavioral-health accommodation for residential treatment of chemical dependency. It belongs to the 100X behavioral-health accommodation family. It should not be described as a generic procedure code or assumed to represent every therapeutic service delivered during the residential stay.
What Is Revenue Code 1002?
Revenue code 1002 represents residential treatment – chemical dependency within the behavioral-health accommodation revenue-code family. On an institutional claim, it helps identify the residential accommodation category, while other claim elements communicate the covered services and billing details required by the payer.
Is Revenue Code 1002 Inpatient or Outpatient?
Revenue code 1002 by itself should not be used as the only determinant of a claim's inpatient or outpatient status. It identifies a residential chemical-dependency accommodation category. The correct claim configuration also depends on the facility type, type of bill, payer contract, authorization, program status, and the other services reported on the claim.
What CPT or HCPCS Code Goes With Revenue Code 1002?
There is no single universal CPT or HCPCS code that must always accompany revenue code 1002. The correct procedure-code configuration depends on the treatment program, payer contract, state rules, covered services, and claim methodology. Never create a national crosswalk from one payer's billing example.
Revenue Code 1002 vs. 0906
| Question | Revenue code 1002 | Revenue code 0906 |
|---|---|---|
| Primary category | Behavioral-health accommodation | Behavioral-health treatment/service |
| General context | Residential treatment – chemical dependency | Intensive outpatient services – chemical dependency |
| Typical level distinction | Residential accommodation | Intensive outpatient service category |
| Still verify | Facility, bill type, authorization, contract and service lines | Procedure code, units, authorization, facility and payer pairing |
Revenue code 1002 is not a standalone billing answer. Validate the facility type, type of bill, treatment program, authorization, covered service lines, procedure codes, dates, units, and payer edits before claim submission.
Modifiers, Units, and Same-Day Substance Abuse Billing
Modifiers should report a true, documented circumstance—not be used simply to force payment through an edit. Before using modifier 59, HF, HA, HB, HD, 93, 95, or another program/credential modifier, confirm that the current code set and responsible payer permit the modifier for that service and setting.
- Modifier 59: Review the current NCCI edit and payer policy. Append it only when a distinct service is supported and the edit permits a modifier.
- HF and other program modifiers: Requirements vary by state Medicaid agency, managed-care organization, and contract. An SUD-related code does not automatically require HF.
- Telehealth modifiers: Use the modifier and place-of-service combination required by the payer for the specific service and date.
- Time and units: Reconcile documented minutes, program attendance, the code's unit definition, payer rounding policy, and daily or episode limits before claim creation.
- Bundled services: Confirm whether counseling, testing, medication, care coordination, or other components are included in a program bundle before billing separately.
Substance Abuse Billing Code Verification Checklist
Every code in this guide is a starting point, not a payer authorization. Run the checks below before the first claim and whenever a payer changes its provider manual, contract, authorization process, fee schedule, or code edits.

What was delivered?
Match the code to the documented assessment, therapy, program day, medication service, detox service, or residential treatment actually provided.
Who and where?
Confirm the rendering provider, facility or program enrollment, certification, place of service, and network status.
Which rule set controls?
Use the current Medicare instruction, state Medicaid manual, managed-care policy, commercial payer manual, and applicable contract.
Does approval match treatment?
Confirm the approved provider, program, dates, service category, level of care, units, and continued-stay requirements.
Which combination?
Validate claim form, bill type, revenue code, procedure code, modifier, units, diagnosis pointers, authorization, and payer ID.
How should it reimburse?
Compare the expected methodology with the contract and remittance so underpayments or incorrect adjustments are not closed without review.
If the issue is broader than code identification, continue with the addiction treatment billing workflow or explore ClaraRCM's substance abuse billing services.
Frequently Asked Questions About Substance Abuse Billing Codes
What codes are used for substance abuse billing?
Substance abuse billing may use CPT codes for professional evaluation and therapy, HCPCS H-codes for SUD and behavioral-health program services, S-codes for certain payer-specific IOP or PHP services, Medicare G-codes for office-based SUD and OTP services, and revenue codes on institutional claims. The correct combination depends on the actual service, provider, setting, payer, state, unit, authorization, contract, and claim format.
Is H0010 a CPT code?
No. H0010 is an HCPCS Level II code describing sub-acute alcohol/drug detoxification in a residential addiction-treatment program. Payer coverage, authorization, facility eligibility, units, and claim requirements must still be verified.
What is the difference between H0010 and H0014?
H0010 describes a residential sub-acute detoxification pathway, while H0014 describes ambulatory detoxification. Both are HCPCS Level II codes. The setting, provider, medical intensity, payer policy, authorization, and billing unit determine which pathway applies.
Is S0201 a CPT code?
No. S0201 is an HCPCS Level II S-code for partial hospitalization services lasting less than 24 hours, described per diem. Payer recognition varies, so verify whether the plan uses S0201, H0035, S9475, or another facility methodology.
What is H0015 used for?
H0015 is an HCPCS Level II code describing an alcohol and/or drug intensive outpatient treatment program. Providers should confirm that the program meets the code definition and verify payer-specific authorization, reimbursement, claim-format, unit, and revenue-code requirements.
Does H0015 always require revenue code 0906?
No. Revenue code 0906 identifies intensive outpatient services for chemical dependency on institutional claims, but the H0015/0906 combination is not a universal rule for every payer, state program, facility, or contract.
What is the difference between H0015 and S9480?
H0015 describes an alcohol/drug intensive outpatient program, while S9480 describes intensive outpatient psychiatric services. The primary program, documented service, payer contract, provider eligibility, diagnosis, and claim instructions determine which code applies.
What is H0018 used for?
H0018 is an HCPCS Level II code for short-term residential behavioral-health treatment in a non-hospital residential program, without room and board, billed per diem. The payer or state determines the covered program requirements, authorization, provider eligibility, and any level-of-care mapping.
Does H0018 include room and board?
No. The H0018 descriptor specifies treatment without room and board. If accommodation charges are separately reportable, the payer contract and institutional billing rules determine the appropriate billing methodology.
Do H0017, H0018, and H0019 equal specific ASAM levels?
Not nationally. Their descriptors identify different residential behavioral-health categories. A payer or state may publish its own ASAM or level-of-care crosswalk, but the same fixed mapping should not be assumed across all plans and states.
What is revenue code 0906?
Revenue code 0906 identifies intensive outpatient services for chemical dependency. It may be used on institutional SUD IOP claims when required by the responsible payer, but the procedure-code pairing, bill type, units, authorization, and facility requirements must also be verified.
What is revenue code 1002 used for?
Revenue code 1002 identifies behavioral-health accommodation for residential treatment of chemical dependency. It is not a standalone procedure code. The facility type, bill type, authorization, contract, covered service lines, and payer-specific claim requirements must also be reviewed.
Is revenue code 1002 inpatient or outpatient?
Revenue code 1002 identifies a residential chemical-dependency accommodation category and should not be used by itself to determine claim status. The correct billing configuration depends on the facility, type of bill, contract, authorization, program classification, and payer instructions.
Can ASAM level alone determine the billing code?
No. ASAM supports clinical level-of-care determination and medical-necessity documentation. Final billing also depends on the actual service, provider, setting, payer, state program, contract, unit, claim form, revenue code, modifiers, and authorization.
Should modifier 59 always be added when SBIRT and psychotherapy occur on the same day?
No. Review the current NCCI edit and the responsible payer's policy. Use modifier 59 only when a truly distinct service is documented and the applicable edit permits a modifier. It should not be added automatically merely to bypass an edit.
Related ClaraRCM Substance Abuse Billing Resources

Andleeb Asghar, Licensed Pharmacist
RCM Specialist & Founder, ClaraRCM
Andleeb Asghar is a pharmacist, medical billing professional, and revenue cycle management specialist with experience in substance use disorder billing, MOUD and OTP workflows, payer-specific coding, denial management, and end-to-end RCM for U.S. healthcare providers.
Last updated: September 15, 2026. This technical reference is educational and is not legal, clinical, coding, reimbursement, or payer-contract advice. CPT content is summarized rather than reproduced. Verify current CPT information through the AMA, HCPCS information through CMS, revenue-code definitions through the applicable institutional billing reference, and coverage through the responsible payer. Code sets, Medicare instructions, Medicaid policies, commercial payer requirements, contracts, and claim edits can change.